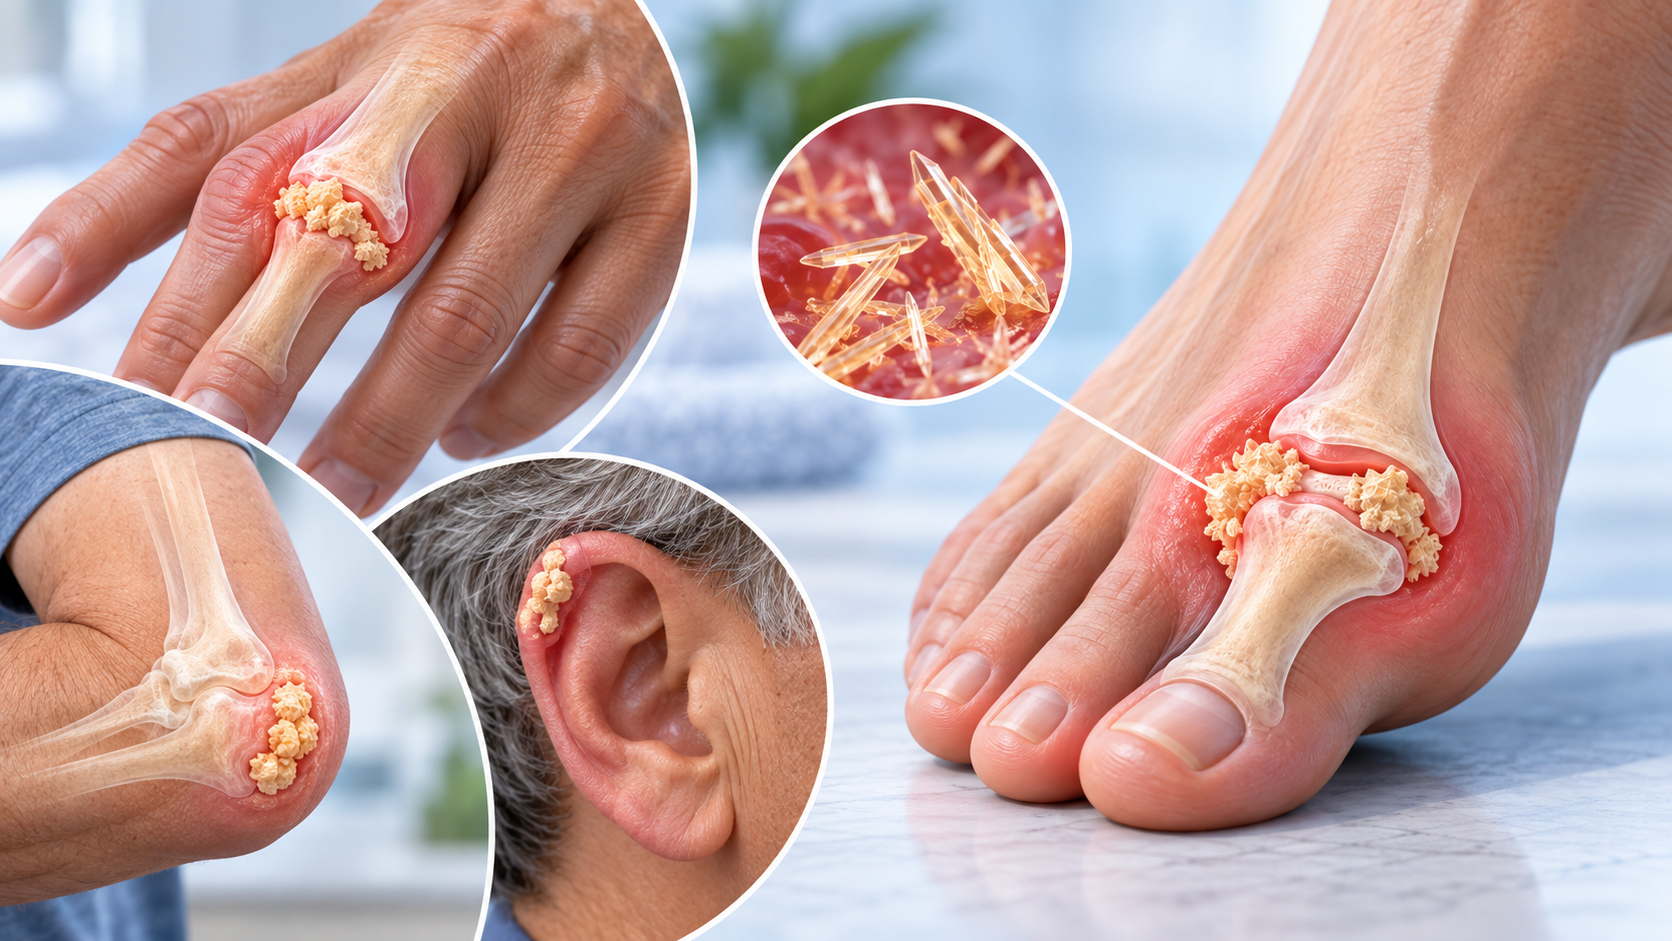
A tophus (plural: tophi) is a deposit of monosodium urate crystals that builds up in tissue in people with gout. Tophi are usually a sign that the body has carried a substantial urate crystal burden for a long time. They may be painless at first, but they can enlarge, damage bone and soft tissue, limit movement, press on nearby structures, or occasionally break through the skin.
The important point is that a tophus is not simply a lump to “treat” on its own. The underlying problem is the urate crystal burden. Long-term treatment aims to keep serum urate low enough, consistently enough, that existing crystals can gradually dissolve and new deposits stop forming.
Already have visible tophi? Use our free Tophi Progress Tracker to map each location, record measurements, take consistent photos and bring a clearer change-over-time record to medical appointments.
What is a tophus, exactly?
A tophus is a localized collection of monosodium urate crystals surrounded by inflammatory and connective tissue. One deposit is a tophus; multiple deposits are called tophi.
Tophi are strongly associated with gout. They generally develop after years of sustained hyperuricemia and crystal deposition, although occasionally a visible tophus may be one of the first clues that someone has gout that was not previously recognized.
If you have a new unexplained lump, do not assume it is a tophus based on a photo or internet description. Other nodules, cysts, deposits and inflammatory conditions can look similar.
What do gout tophi look and feel like?
Tophi can vary a lot in appearance. They may feel firm or hard under the skin and can range from very small deposits to much larger irregular lumps. Some are skin-colored. Others may have a pale, yellow-white or chalky appearance close to the surface.
A tophus may be:
- painless or only mildly tender;
- firm, lumpy or irregular rather than soft;
- single or part of a cluster;
- associated with stiffness or reduced motion when it sits near a joint or tendon;
- covered by normal-looking skin, stretched skin, or thinner irritated skin;
- occasionally open or draining white, chalky material.
Visible appearance alone cannot confirm the diagnosis. If the lump is new, changing quickly, unusually painful, infected-looking or in an unexpected location, medical evaluation matters.
Where do tophi form?
Tophi can occur in and around joints, tendons, cartilage and other soft tissues. Common visible locations include:
- fingers and knuckles;
- toes and feet;
- elbows, especially around the olecranon area;
- ankles and Achilles tendon area;
- ears;
- hands and wrists;
- other joints affected by longstanding gout.
Tophi can also exist deeper in tissue where they are not obvious from the surface. Ultrasound and dual-energy CT can sometimes identify urate crystal deposits that are not visible externally. See our guide to where gout and urate deposits can affect the body.
Are tophi always painful?
No. One of the confusing things about tophi is that a substantial deposit can be relatively painless. Pain does not reliably tell you how much crystal burden is present.
Tophi can become painful when they stretch surrounding tissue, become inflamed, interfere mechanically with a joint or tendon, compress a nearby nerve, break down through the skin, or are complicated by infection.
What do tophi mean about the severity of gout?
Visible tophi generally indicate advanced or longstanding urate crystal deposition. In modern gout management, their presence is a strong reason to discuss long-term urate-lowering therapy rather than relying only on medicines that treat individual flares.
The American College of Rheumatology strongly recommends urate-lowering therapy for people with one or more subcutaneous tophi. That is different from taking an anti-inflammatory medicine only when an attack starts. Flare medicines can reduce pain and inflammation, but they do not remove the underlying urate crystal burden.
Can tophi shrink or go away?
Yes. Tophi can shrink and, in some people, eventually resolve when serum urate is kept low enough over time. The process is not instant. A visible tophus represents a large amount of deposited crystal, so improvement commonly takes months to years rather than days or weeks.
The rate varies with factors such as:
- how low serum urate is kept;
- how consistently the target is maintained;
- the size and number of tophi;
- how long the deposits have been present;
- kidney function and other medical factors;
- which urate-lowering treatment is being used.
For more on the underlying process, see how long gout crystals can take to dissolve.
What serum urate target is used when someone has tophi?
Guidelines use a treat-to-target approach rather than a fixed medication dose for everyone.
| Guideline | Serum urate approach |
|---|---|
| American College of Rheumatology | Recommends titrating urate-lowering therapy to achieve and maintain serum urate below 6 mg/dL (360 micromol/L). |
| NICE | Recommends a target below 6 mg/dL (360 micromol/L), and says a lower target below 5 mg/dL (300 micromol/L) can be considered for people with tophi or chronic gouty arthritis. |
This is one reason tracking serum urate over time can be more useful than focusing on a single reading.
Which medicines are used to treat tophaceous gout?
The treatment goal is sustained urate lowering. The specific drug and dose depend on the person, kidney function, other medical conditions, prior response and clinician judgment.
Allopurinol
Allopurinol is generally the preferred first-line urate-lowering medicine in U.S. guidelines. The dose may need to be gradually adjusted while serum urate is monitored.
Febuxostat
Febuxostat is another xanthine oxidase inhibitor that can lower serum urate and may be used when allopurinol is not appropriate or does not achieve the desired result.
Pegloticase
Pegloticase is an intravenous therapy used for selected people with severe, refractory gout. It is not first-line treatment. ACR guidance reserves it for people in whom other urate-lowering strategies have failed and who continue to have substantial disease activity such as frequent flares or nonresolving tophi.
See our fuller guide to allopurinol, febuxostat and treat-to-target urate-lowering therapy.
Do colchicine, ibuprofen or steroids dissolve tophi?
No. These medicines can be very useful for treating or preventing the inflammation of gout flares, but they are not the medicines that progressively remove the urate crystal burden.
This distinction matters: someone can have fewer painful attacks while still having urate deposits unless long-term serum urate is adequately controlled.
Can diet, water or supplements dissolve a tophus?
Diet, weight management, alcohol reduction and hydration can be useful parts of gout care, but established tophi usually represent a crystal burden that requires a medical urate-lowering strategy.
There is no food, drink, “flush,” cleanse or supplement that has been shown to rapidly dissolve an established tophus. Be especially cautious with products promising to melt, purge or flush gout crystals quickly.
Lifestyle changes are best thought of as supporting long-term urate control, not replacing indicated urate-lowering medication.
How are tophi diagnosed?
Sometimes the combination of a typical appearance, location and known gout history makes the diagnosis clinically convincing. When the diagnosis is uncertain, clinicians may use:
- physical examination;
- aspiration or sampling of material to identify monosodium urate crystals;
- ultrasound;
- dual-energy CT (DECT);
- X-rays when joint or bone damage is a concern;
- serum urate testing as part of the overall assessment.
Serum urate alone cannot prove that a particular lump is a tophus.
What can look like a tophus?
An unexplained nodule can have many causes. Depending on location and appearance, possibilities can include cysts, rheumatoid nodules, calcific deposits, benign skin growths, infected collections and other soft-tissue masses.
That is why a “looks like my photo” comparison is not enough for diagnosis, particularly if you have never been diagnosed with gout or the lump appeared before any typical gout symptoms.
What happens if a tophus opens or drains?
A tophus can occasionally erode through the skin and release white or chalky material. This should not be squeezed, punctured or treated like a pimple.
Contact a clinician promptly if a suspected tophus opens or drains, especially if there is increasing redness, warmth, swelling, worsening pain, fever or foul-smelling drainage. Once the skin barrier is broken, infection and wound-care issues become more important.
Can tophi damage joints even when they do not hurt?
Yes. Tophi can erode bone and damage surrounding soft tissue. They can also interfere mechanically with joint movement or tendon function. This is one reason clinicians take visible tophi seriously even when the person is not having constant pain.
Tophi fit into the later stages of gout described in our guide to flares, intercritical gout, tophi and joint damage.
When is surgery used for gout tophi?
Most tophi are treated by controlling serum urate rather than by removing every deposit surgically. Surgery may be considered in selected cases when a tophus causes problems that cannot reasonably wait for medical shrinkage alone, such as:
- major loss of joint or tendon function;
- severe mechanical interference or deformity;
- nerve compression;
- recurrent skin breakdown or ulceration;
- infection concerns;
- severe pain or disability from the mass itself.
Surgery does not correct the underlying tendency to form urate crystals, so long-term urate management remains important afterward.
How can you tell whether a tophus is actually getting smaller?
Memory is surprisingly poor at judging slow physical change. This is where we borrowed a useful idea from dermatology mole mapping: create a baseline and compare the same spot in a consistent way.
Our free Tophi Progress Tracker lets you:
- give each tophus a stable ID such as T1 or T2;
- mark the location on a body map;
- measure it in millimeters;
- take repeat photographs using a similar angle, distance and lighting;
- record whether the skin is intact, irritated, open or draining;
- record pain and effect on movement or function;
- place those changes beside your serum urate and treatment history.
The tracker is not a diagnostic tool and a photograph cannot prove that a treatment is working. Its value is giving you and your clinician a more reliable longitudinal record than “I think it looks smaller.”
When should someone with tophi see a rheumatologist?
Tophi are a reasonable reason to involve a clinician experienced in long-term gout management, particularly when:
- serum urate remains above target despite treatment;
- tophi continue to grow or new ones appear;
- flares continue despite urate-lowering therapy;
- there is significant joint damage or functional limitation;
- kidney disease or medication intolerance complicates treatment;
- advanced therapy such as pegloticase is being considered;
- the diagnosis is uncertain.
See what type of doctor treats gout and when a rheumatologist may help.
What should you do next if you think you have a tophus?
- Confirm what the lump is. Do not rely on appearance alone if it has not been medically evaluated.
- Know your serum urate trend. One reading is less useful than repeated measurements in context.
- Discuss treat-to-target urate lowering. Visible tophi generally mean long-term crystal reduction matters.
- Track visible deposits consistently. Use measurements and photos rather than memory.
- Get help promptly for skin breakdown or possible infection. Do not wait for a routine tracking interval.
If gout keeps returning as well, read why recurrent gout flares happen and what they may mean.
This article is educational and is not a substitute for diagnosis or individualized medical advice. Do not start, stop or change prescription gout treatment based only on information from this page.
Sources
- American College of Rheumatology: 2020 Guideline for the Management of Gout
- NICE NG219: Gout – diagnosis and management
- NIAMS: Gout diagnosis, treatment and steps to take
- Cochrane: Interventions for tophi in gout
- Chhana & Dalbeth: The gouty tophus – a review
- Cleveland Clinic: Gout Tophi
Evidence checked September 2026.